Worried by a diabetic nephropathy biopsy? Learn how kidney changes are reported and what questions can guide the next visit.
Diabetic nephropathy biopsy results describe kidney changes caused by diabetes and show how much permanent scarring or active injury is present. A kidney biopsy is usually done when the clinical picture is not completely typical, when kidney function changes quickly, or when doctors need to rule out another disease. The wording can feel technical because pathologists are describing tiny structures that filter blood, hold back protein, and support kidney tissue.
Receiving a biopsy result can feel frightening, especially when words such as sclerosis, fibrosis, or basement membrane appear without much explanation. Those words do not automatically mean failure is imminent. They are the pathologist’s way of mapping what has happened in the kidney, how widespread it is, and whether another process may be contributing. Clear understanding can turn a confusing report into a practical conversation with the kidney specialist.
Diabetic Nephropathy Biopsy — What It Actually Means
A diabetic nephropathy biopsy is an examination of a tiny core of kidney tissue under the microscope to look for changes commonly caused by long-standing diabetes. In a kidney biopsy report, the pathologist usually describes the glomeruli, tubules, blood vessels, and surrounding support tissue. The glomeruli are the kidney’s filtering units, similar to coffee filters that let water and small dissolved substances pass while keeping larger proteins in the bloodstream. Diabetes can thicken and scar these filters over time.
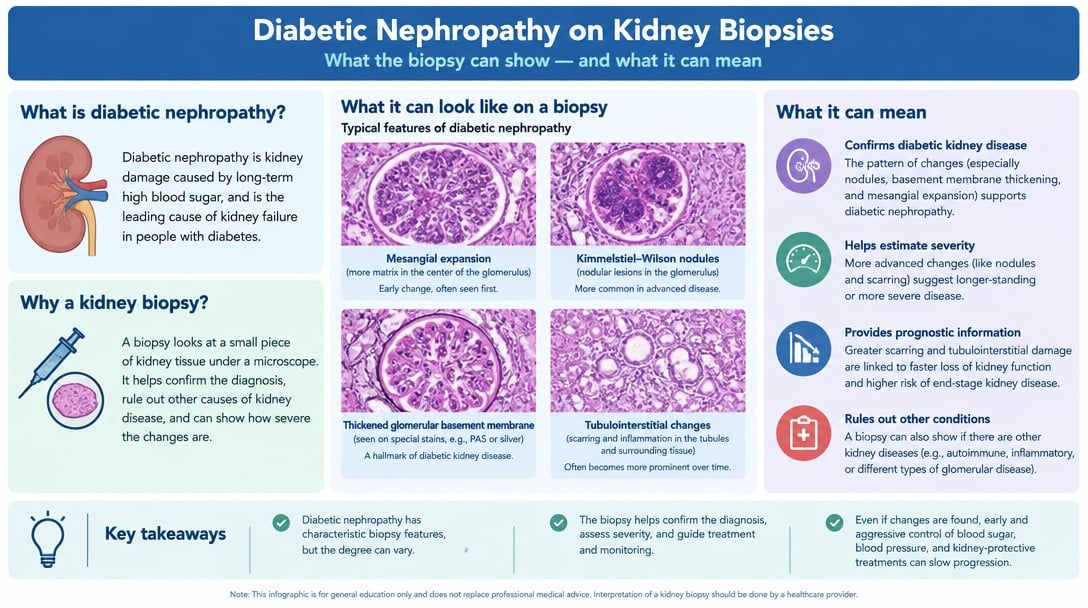
The classic changes of diabetic kidney disease include thickening of the glomerular basement membrane, mesangial expansion, and scarring of glomeruli. The glomerular basement membrane is a delicate filter layer that can become abnormally thick in diabetes. Mesangial expansion means that the support material within the filtering unit has increased, narrowing the usable filtering space. When the pattern is advanced, rounded scar-like deposits called nodular glomerulosclerosis may be seen.
A pathology report may also mention whether the findings are diffuse, nodular, mild, moderate, or severe. These words help the treating team connect the microscope findings with protein in the urine, blood pressure, creatinine, and the estimated glomerular filtration rate. For patients trying to understand the format of the result, what a pathology report is can help explain why reports are written in sections. In plain terms, the diabetic nephropathy biopsy is not just naming the disease; it is measuring the footprint diabetes has left in the kidney.
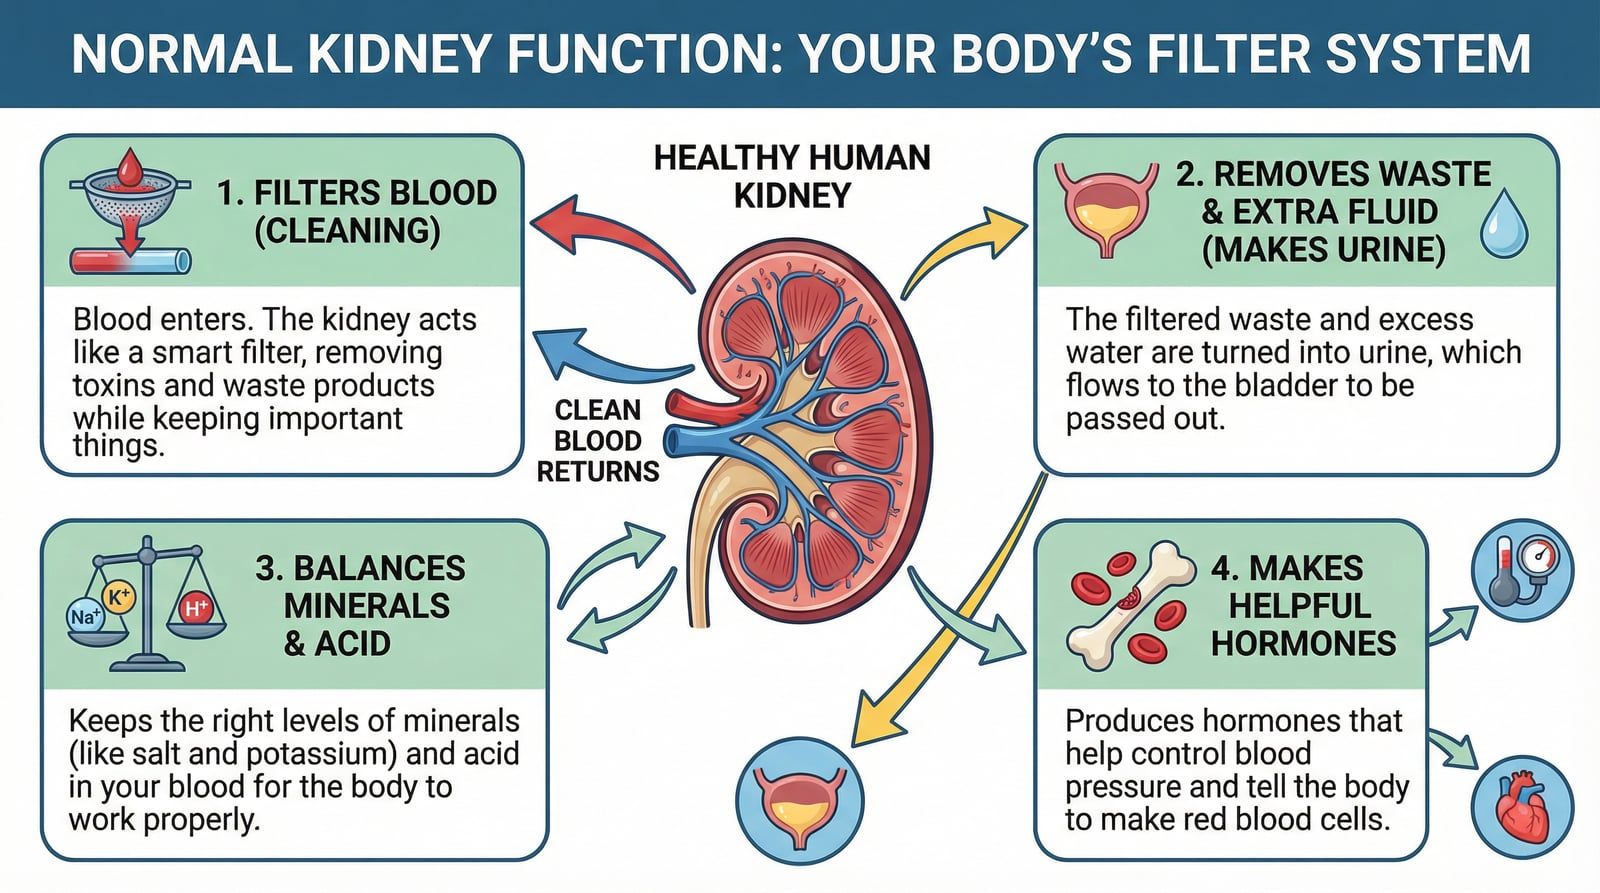
Why The Kidney Biopsy Report Shows These Changes
A kidney biopsy report shows these findings because diabetes affects small blood vessels throughout the body, including the fine capillaries inside each glomerulus. High blood sugar, high blood pressure, and metabolic stress can injure the filtering barrier over years. The glomerular basement membrane often becomes thicker before a person feels any symptoms. Protein in the urine may be one of the earliest outward signs that the filter has become leaky.
Under the microscope, pathologists look for mesangial expansion, nodular glomerulosclerosis, and global or segmental sclerosis. Global sclerosis means an entire glomerulus is scarred, while segmental sclerosis means only part of it is scarred. Interstitial fibrosis describes scarring in the tissue between tubules, and tubular atrophy means some tubules have become shrunken or damaged. These features matter because interstitial fibrosis and tubular atrophy often correlate with chronic, less reversible kidney injury.
The report also evaluates blood vessels, because diabetic kidney disease often affects arteries and arterioles. Terms such as arteriosclerosis, arteriolar hyalinosis, and vascular sclerosis describe thickening or hardening of vessel walls. A diabetic nephropathy biopsy may also be performed to check for another condition, such as IgA nephropathy, membranous nephropathy, lupus nephritis, or medication-related injury. When the findings are not purely diabetic, the pathology report may list more than one diagnosis so treatment can be tailored more accurately.
How Serious Is A Diabetic Nephropathy Biopsy Finding?
The seriousness of a diabetic nephropathy biopsy depends on the pattern and amount of damage reported. Mild mesangial expansion with limited scarring usually carries a different meaning than widespread nodular glomerulosclerosis with extensive interstitial fibrosis. A diabetic nephropathy biopsy does not predict the future by itself; it adds tissue-level evidence to blood tests, urine protein measurements, blood pressure history, and diabetes control. The most useful interpretation comes from combining all of those pieces.
Pathologists often grade or classify diabetic kidney disease using recognized systems, especially when glomerular changes are prominent. Early changes may include thickening of the glomerular basement membrane, sometimes visible only with special techniques such as electron microscopy. More advanced changes may include prominent mesangial expansion, Kimmelstiel-Wilson nodules, and more glomeruli replaced by scar. If the kidney biopsy report mentions extensive interstitial fibrosis, that usually suggests chronic injury that may not fully reverse, even when treatment improves stability.
Serious does not always mean hopeless. A diabetic nephropathy biopsy can reveal how much kidney tissue remains functional and whether there is a treatable second process. For example, if the biopsy shows diabetic kidney disease plus an inflammatory glomerulonephritis, the treatment plan may change. If it shows mostly chronic diabetic scarring, the focus often shifts to slowing progression, reducing urine protein, controlling blood pressure, and protecting remaining kidney function.
What Happens Next: Treatment And Monitoring
After a diabetic nephropathy biopsy, the nephrologist usually compares the biopsy findings with kidney function tests, urine albumin or protein levels, blood pressure, diabetes history, and medications. The goal is to decide whether the result fits expected diabetic kidney disease or whether another diagnosis needs treatment. A kidney biopsy report may also guide how closely kidney function should be monitored. Reports with significant scarring often lead to careful follow-up because the kidney reserve may be lower.
Treatment is individualized and may include tighter blood pressure control, medicines that reduce protein leakage, diabetes medications with kidney-protective benefits, cholesterol management, and dietary guidance. The pathology report does not prescribe treatment directly, but it helps show how much chronic damage has accumulated. When the glomerular basement membrane is thickened but scarring is limited, prevention of progression may be a major focus. When interstitial fibrosis is extensive, the plan may emphasize preserving remaining function and preparing early for possible future needs.
Monitoring often includes repeated creatinine, estimated glomerular filtration rate, urine albumin-to-creatinine ratio, and blood pressure checks. The diabetic nephropathy biopsy provides a baseline tissue diagnosis, but day-to-day progress is usually followed with blood and urine testing. Patients who feel overwhelmed by the language may benefit from reading how to read a pathology report with confidence. That type of preparation can make the next nephrology appointment more focused and less intimidating.
Questions To Ask Your Doctor Or Pathologist
- Does the diabetic nephropathy biopsy show only diabetic kidney disease, or is another kidney disease also present?
- How many glomeruli were sampled, and was the sample adequate for diagnosis?
- How much interstitial fibrosis and tubular atrophy are described in the kidney biopsy report?
- Does the report mention nodular glomerulosclerosis, and what does that mean for kidney function?
- Was the glomerular basement membrane evaluated by electron microscopy?
- How do the biopsy findings compare with the amount of protein in the urine?
- Would a second review by a kidney pathologist change treatment decisions?
These questions can help turn the pathology report into a practical plan. The most helpful appointment usually links the biopsy findings to specific clinical decisions, such as medication changes, follow-up timing, and risk reduction. A patient does not need to master every microscopic term to ask strong questions.
If the diagnosis seems unexpected, if another disease is listed, or if treatment decisions are major, a second pathology opinion may be appropriate. Guidance on when to get a second pathology opinion can help patients decide whether review by a subspecialist kidney pathologist makes sense. A second review is especially reasonable when the biopsy sample is limited, the report contains more than one diagnosis, or the clinical story and biopsy result do not seem to match.
Frequently Asked Questions
What does diabetic nephropathy on biopsy mean?
Diabetic nephropathy on biopsy means the kidney tissue shows microscopic changes commonly caused by diabetes. A diabetic nephropathy biopsy may show thickened filtering membranes, mesangial expansion, vascular changes, and scarring. The result helps confirm whether diabetic kidney disease explains the patient’s kidney problems. It may also show whether another kidney disease is present at the same time.
Can a kidney biopsy tell how advanced diabetic kidney disease is?
A kidney biopsy can help estimate how advanced diabetic kidney disease is by showing the amount of glomerular scarring, tubular atrophy, and interstitial fibrosis. The kidney biopsy report may describe mild, moderate, or severe chronic damage. This information is interpreted together with creatinine, urine protein, and blood pressure. The biopsy is one piece of the overall kidney health picture.
What is nodular glomerulosclerosis in diabetes?
Nodular glomerulosclerosis is a pattern of rounded scar-like deposits within the kidney filtering units. It is a classic feature of more established diabetic kidney disease, although pathologists still consider the full pattern before making a diagnosis. In a diabetic nephropathy biopsy, nodular glomerulosclerosis can support the diagnosis when other diabetic changes are also present. The finding often suggests chronic injury rather than a sudden short-term problem.
Does diabetic nephropathy biopsy mean dialysis is needed?
A diabetic nephropathy biopsy does not automatically mean dialysis is needed. Dialysis decisions depend mainly on kidney function, symptoms, lab results, fluid balance, and overall clinical status. Some biopsy reports show chronic scarring but enough remaining function for years of monitoring and kidney-protective treatment. The treating nephrologist can explain how the biopsy result fits the patient’s current kidney function.
Should a diabetic kidney biopsy get a second opinion?
A second opinion can be helpful when the pathology report is complex, unexpected, or likely to affect major treatment decisions. It may also be useful if the biopsy suggests more than diabetic kidney disease. Patients can ask whether the slides were reviewed by a renal pathologist with kidney biopsy expertise. Practical steps are described in how to get a second opinion on a pathology diagnosis.
A diabetic nephropathy biopsy can sound severe because the language is microscopic and technical. In practice, the report is a map: It shows what is scarred, what may still be protected, and whether another condition needs attention. Honest Pathology consultations can help patients and families understand the wording of a kidney biopsy report before important treatment conversations.
References:
National Cancer Institute — Pathology Reports
MedlinePlus — Diabetic Kidney Problems
NCBI Bookshelf — Medical Reference Books