
Imaging Detection
Ultrasound, CT, or MRI may identify a renal mass and describe its location and radiologic extent.
Get a clearer explanation of the diagnosis, renal tumor type, WHO/ISUP grade when applicable, tumor size, necrosis, sarcomatoid or rhabdoid features, renal sinus or vein involvement, margins, lymph nodes, and molecular findings documented in your report.
This educational consultation explains your existing written pathology report. It does not provide a new diagnosis, written report, official document, treatment plan, or replacement for your treating clinicians.
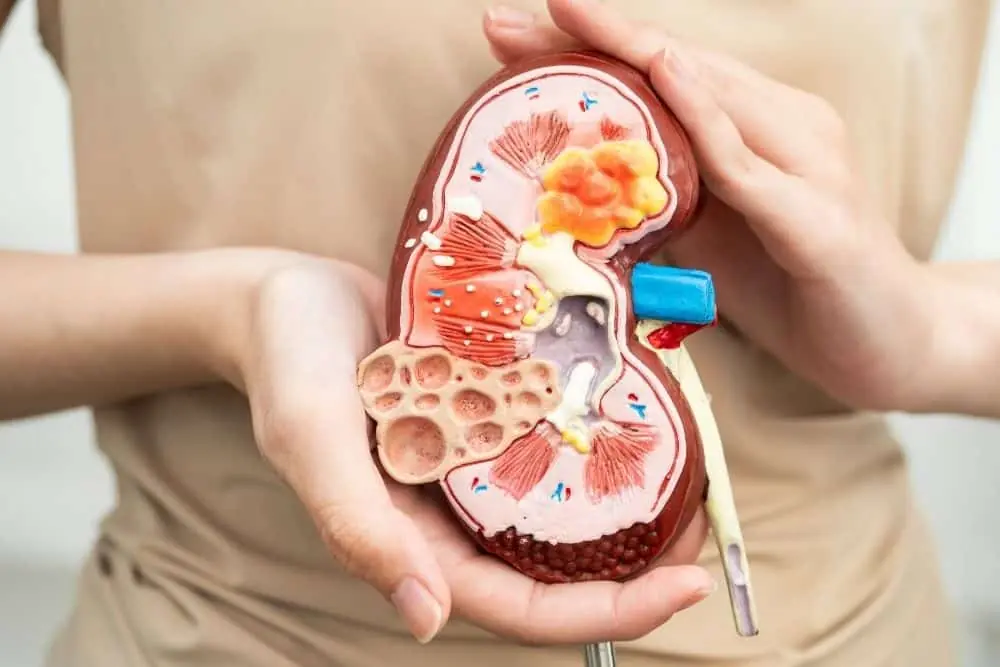
Imaging often identifies a kidney mass, but pathology examines sampled or removed tissue to establish the tumor type and document specimen-specific features.
Ultrasound, CT, or MRI may identify a renal mass and describe its location and radiologic extent.
Some masses undergo needle biopsy; others are evaluated after partial or radical nephrectomy.
The pathologist identifies the tumor type and reports grade, size, necrosis, invasion, margins, and nodes when assessable.
Imaging, pathology, laboratory results, health history, and operative findings are considered together by the care team.
A needle biopsy samples part of a kidney mass. A partial or radical nephrectomy examines substantially more tissue and can assess size, extent, margins, and other structures.
The report addresses the tissue present in a limited core sample.
The removed tumor and surrounding tissues may answer additional staging questions.
The findings available depend on whether the specimen is a core biopsy, partial nephrectomy, radical nephrectomy, lymph node, or metastatic-site sample.
“Kidney cancer” includes multiple tumor types. Grade systems and expected report elements are not identical for every renal tumor.
The report may identify clear cell, papillary, chromophobe, or another renal tumor type based on morphology and supporting studies.
For tumor types where this grading system applies, grade reflects nuclear and nucleolar features and may include sarcomatoid or rhabdoid morphology.
A nephrectomy report records the largest tumor dimension and whether one or multiple tumors are present.
Microscopic tumor necrosis may be recorded separately from nonviable tissue caused by prior treatment or other changes.
These high-grade morphologic patterns may occur in different renal cell carcinoma types and are documented when present.
The report may evaluate renal sinus, perinephric fat, renal vein or segmental branches, adrenal gland, or other submitted structures.
Margins depend on the procedure and may include renal parenchymal, soft-tissue, vascular, or ureteral margins.
When nodes are submitted, the report documents the number examined and involved and may record the size of the largest deposit.
Review the tumor type, grade, size, invasion findings, margins, nodes, specimen limitations, and pending results in your existing kidney pathology report during a secure virtual consultation.
For renal cell carcinoma, the pT category uses tumor size and involvement of specific anatomic structures. It is one part of stage and should be read with nodes, metastasis, imaging, and clinical information.
A tumor can move into a higher pT category because of anatomic invasion even when its size is smaller.
Microscopic involvement of renal sinus fat or specified venous structures can affect the pT category.
The pathology pT category does not by itself establish the complete stage group or treatment plan.
A nephrectomy report may document whether the tumor is confined to the kidney or involves specified vascular, fatty-tissue, or adjacent structures.
The renal sinus contains vessels and fat near the kidney hilum. Tumor invasion here is assessed carefully in nephrectomy specimens.
The report may document tumor in the renal vein or its segmental branches and distinguish it from other findings.
Tumor extension into fat around the kidney is reported when identified and is interpreted with Gerota fascia involvement.
Direct contiguous invasion is distinguished from a separate metastatic deposit and may affect classification.
Margin status, submitted lymph nodes, tumor size, and specified sites of invasion are documented separately. The complete stage requires information beyond the nephrectomy report alone.
Additional testing varies according to the tumor morphology, differential diagnosis, patient age, family history, and clinical question.
Immunostains may help establish renal origin or distinguish among renal tumor types and mimics.
Selected tumors may undergo molecular testing to refine classification or document specific alterations.
Germline testing is separate from tumor testing and may be relevant when age, tumor pattern, personal history, or family history suggests hereditary risk.
Get a patient-friendly explanation of studies already documented in your reports and identify which results may still be pending or reported separately.
A kidney pathology report may answer many important questions, but it does not provide the complete stage or clinical plan on its own.
The tumor type, grade when applicable, size, necrosis, sarcomatoid or rhabdoid features, invasion, margins, and nodes may be documented when assessable.
Immunohistochemistry, molecular testing, outside consultation, genetic testing, or another specimen may be pending or separately reported.
Imaging, laboratory results, operative findings, health history, and evaluation by the treating team provide wider clinical context.
A pathology report consultation helps you understand terminology and findings already documented, so you can approach conversations with your treating team with greater context and more focused questions.
Submit the pathology report and relevant records requested for the consultation.
Discuss the report during a private virtual appointment and ask questions about the documented findings.
Better understand the terminology and prepare questions to discuss with your treating care team.
A report explanation and a formal microscopic second opinion are different services. Clear boundaries help you choose the appropriate option.
The right option depends on whether you need help understanding written results or an independent review of pathology slides, tissue, or digital images.
These answers provide general educational information. Individual reports vary according to specimen, procedure, tumor type, prior treatment, additional testing, and wider clinical situation.
No. Renal tumors include multiple histologic types with different microscopic and molecular features. The exact diagnosis should come from the pathology report.
It is a microscopic grading system used for applicable renal cell carcinoma types. It is separate from the pT category and complete stage.
No. A core biopsy samples only part of a mass and usually cannot evaluate the full tumor size, margins, or complete anatomic extent.
They are high-grade morphologic patterns that may occur in different renal cell carcinoma types and are documented separately when present.
It means tumor extends into specified tissues or vessels in the renal sinus near the kidney hilum. The exact report wording determines what was identified.
It means tumor reaches an inked specimen edge. The meaning depends on the procedure and the specific margin involved.
Age, bilateral or multifocal tumors, specific histology, personal history, or family history may prompt a separate hereditary-risk evaluation by the clinical team.
A formal second opinion may be appropriate when findings are complex, uncertain, unexpected, or when independent examination of the original slides or tissue could provide additional value.
Meet online with a pathologist who can explain the tumor type, grade, size, invasion findings, margins, lymph nodes, specimen limitations, molecular studies, and questions raised by your existing report.
Educational support only. This service does not replace your treating physician, urologist, urologic oncologist, surgeon, radiologist, genetic counselor, or medical care team.
